
Physiotherapists Are Now Custodians Under Alberta’s Health Information Act

Physiotherapists Are Now Custodians Under Alberta’s Health Information Act

Physiotherapists Are Now Custodians Under Alberta’s Health Information Act

Guest Author – Samia Arshad – 2nd Year Practicum HIM Student (SAIT) 

Effective June 22, 2026, all registered physiotherapists in Alberta are designated custodians under the Health Information Act (HIA). The change comes through the proclamation of the Health Statutes Amendment Act, 2025 (No.2) together with Ministerial Order M.O. 19/2026.

What is New?

Until now, physiotherapists were subject to several different privacy laws, depending on the setting of their practice.  Now, all health information that a physiotherapist collects, uses, and discloses when providing health services will be subject to the HIA, regardless of where they practice.

What is a Custodian?

A custodian is a healthcare provider who is accountable for the health information in their custody or control.

Unlike the Personal Information and Protection Act (PIPA), which is consent based, the HIA is authority based. The HIA authorizes custodians to collect, use, and disclose health information for purposes set out in the Act, and requires them to identify those purposes at the point of collection.

By default, every physiotherapist is a custodian. However, when a physiotherapist works with another custodian–for example, in a multi-disciplinary community practice, or as an employee of a hospital or other custodian—they may act as an affiliate if the named custodian accepts the responsibility to ensure that the personal health information (PHI) will be managed in compliance of the HIA.

When a custodian declares themselves as an affiliate:

  • The relationship between the affiliate and custodian must be clearly established in writing.
  • Roles and responsibilities for managing health information must be clearly defined.

Custodians may delegate their responsibility to another custodian.
You can not abdicate your responsibilities as a custodian.

What Are a Custodian’s Responsibilities?

The HIA sets out several legal duties that every custodian must meet. As a custodian, you are responsible to:

  • Safeguard health information with reasonable administrative, technical, and physical measures (duty to protect, s. 60).
  • Collect only what is necessary for an authorized purpose and disclose the least amount of information needed.
  • Complete and submit Privacy Impact Assessments (PIAs) to the Office of the Information and Privacy Commissioner (OIPC) before implementing new or changed administrative practices or information systems (s. 64).
  • Put Information Manager Agreements in place with third-party providers such as EMR vendors (HIR s. 7.2). See the Top 3 Agreements Your Healthcare Practice MUST Have (and Why).
  • Report privacy breaches where there is a risk of harm. Penalties for failing to comply with mandatory privacy breach notification requirements range from $2,000 to $500,000.
  • Provide patients access to their records, respond to correction requests, and apply the chart-copy fees set in the HIA and HIR.
  • Create or review and update collection statements, privacy policies and procedures to ensure compliance with the HIA.

How Will This Impact Physiotherapists?

The impact depends on where you practise.

Public sector (AHS, hospitals, other agencies subject to POPA and HIA) Many physiotherapist will operate as affiliates under an existing custodian under the HIA.  Ask your organization’s privacy officer if you’re not sure.

Private practice (previously subject to PIPA, now HIA) Physiotherapists must create or review, and update your privacy collection statement, policies and procedures, PIAs, and EMR/third-party agreements to meet HIA requirements.

Physiotherapists are required to submit a PIA to the OIPC before implementing a new practice or system, or a change to an existing one (HIA s. 64).

How Will this Affect Other Healthcare Providers?

This change allows physiotherapists to share health information with other custodians–including physicians, pharmacists, chiropractors, dentists, nurses, and others–for the patients’ continuing care and treatment without additional consent from the patient, where authorized by the HIA.

Where to Get Help?

The College of Physiotherapists’ recommends that members prepare your PIAs now, as they take significant time to complete.

Resources are available from the College, the Office of the Information and Privacy Commissioner (OIPC) and Information Managers to help physiotherapists understand and meet their new responsibilities under the HIA.

References and Resources

College of Physiotherapists of Alberta.

Government of Alberta.

Information Managers Ltd.

Office of the Information and Privacy Commissioner of Alberta. Health Information Act resources. https://oipc.ab.ca/

How Often Should Privacy Awareness Training Be Provided

How Often Should Privacy Awareness Training Be Provided

What Is the Best Practice for Privacy Awareness Training?

Privacy awareness training should not be a one-time event. Best practice is to provide privacy awareness training annually and reinforce key concepts throughout the year.

This expectation is frequently reinforced by privacy regulators, including the Office of the Information and Privacy Commissioner (OIPC), in privacy breach investigation reports. Organizations are expected to demonstrate that privacy awareness is an ongoing program rather than a single training activity.

As a best practice, I recommend that all employees complete comprehensive privacy awareness training at least annually, supplemented by ongoing refresher activities throughout the year. Annual training helps reinforce foundational concepts, demonstrate accountability, and ensure your organization can show consistent compliance if it is ever reviewed.

Most Privacy Breaches are Caused by People, Not Technology

Privacy training is often treated as:

  • A checkbox
  • A one-time event
  • Something to “get done”

However, most privacy breaches are caused by people, not technology. Common examples include:

  • Curiosity snooping
  • Misdirected communication
  • Lack of awareness
  • Inconsistent practices
  • Failure to follow established procedures

Technology plays an important role in protecting information, but employees make decisions every day about how information is collected, used, disclosed, and safeguarded. Effective privacy awareness training helps employees make the right decisions when faced with real-world situations.

Privacy awareness training is one of the most effective ways to prevent avoidable privacy breaches.

Privacy Awareness Training Is Your First Line of Defense

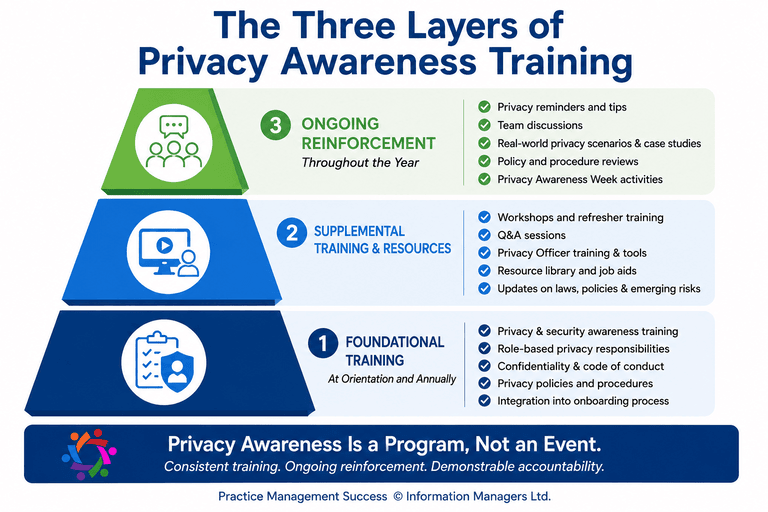
To make privacy awareness training practical and effective, think of it as a program with three layers:

1. Foundational Training (At Orientation and Annually)

Provide comprehensive privacy and security awareness training to all employees, vendors, and business associates at onboarding. The Corridor Interactive Healthcare Essentials course is an easy-to-implement solution that supports consistent training across the organization:

Privacy awareness training should then be repeated annually for all staff. Alternate the annual content with the Corridor Refresher Privacy Awareness Training (PAT) and with supplemental training and resources to keep content engaging, relevant and current.

2. Supplemental Training and Resources

Annual training provides the foundation, but employees benefit from additional learning opportunities throughout the year. Information Managers’ Practical Privacy Officer Strategies training includes a module on designing and implementing a privacy awareness training plan that you can reuse year after year. This on-line course is ideal for privacy officers and clinic managers.

Practice Management Success membership includes monthly Q&A sessions and practical training topics you can use for refresher training throughout the year. Workshop-on-demand topics include privacy breach management, release of information best practices, AI Governance, and more!

3. Ongoing Reinforcement (Throughout the Year)

The most effective privacy programs keep privacy visible throughout the year.

Reinforce key concepts through:

  • Short privacy reminders
  • Team discussions
  • Privacy breach case studies
  • Staff meetings
  • Policy and procedure reviews
  • Privacy Awareness Week activities

Use real-world privacy scenarios and your organization’s policies and procedures as discussion tools to keep expectations clear and top of mind.

These small but consistent reminders help employees apply privacy principles in their day-to-day work and reduce the risk of privacy incidents.

What Regulators Expect: Demonstrable Accountability

Privacy awareness training is not simply a best practice—it is often a factor considered by privacy regulators when investigating privacy breaches.

For example, in Ontario PHIPA Administrative Monetary Penalty, a healthcare worker repeatedly accessed patient records without authorization. The Information and Privacy Commissioner emphasized the organization’s responsibility to implement safeguards, monitor compliance, and ensure employees understand their privacy obligations. While policies existed, the case highlights the importance of ongoing privacy awareness, monitoring, and reinforcement to prevent curiosity snooping and other inappropriate access.

Similarly, privacy commissioners across Canada frequently examine whether organizations can demonstrate that employees received privacy training and understood their responsibilities. During investigations, regulators often ask for evidence such as training records, attendance logs, signed confidentiality agreements, policy acknowledgements, privacy reminders, and documentation of corrective actions.

This is where many organizations struggle. They may have policies and procedures, but they cannot demonstrate that employees reviewed them, understood them, or applied them in practice.

When a privacy breach occurs, documentation matters. Organizations that can show a planned privacy awareness program, annual training, ongoing reminders, and documented participation are in a much stronger position to demonstrate due diligence and accountability.

The lesson is simple: privacy awareness training should not be viewed as a one-time event. It should be an ongoing program that helps employees recognize risks, make good decisions, and protect patient information every day.

Privacy regulators and group practice reviews increasingly focus on an organization’s ability to demonstrate accountability.

You must be able to demonstrate:

  • Training is planned and intentional
  • Staff participated in training
  • Staff understood key concepts
  • Training is relevant to employee roles
  • Privacy awareness activities occur throughout the year

This concept is often referred to as demonstrable accountability.

Demonstrable accountability means having evidence that your privacy program is working—not simply having written policies and procedures sitting on a shelf.

See Why “Demonstrable Accountability” Matters

Need Help to Create Your Privacy Awareness Program?

In the Practical Privacy Officer Strategies training, you quickly create a privacy awareness plan that can be reused and updated each year.

A successful privacy awareness program combines annual comprehensive training with ongoing reinforcement throughout the year. This approach helps reduce privacy risks, supports employee confidence, and demonstrates the due diligence and accountability expected by regulators, patients, and healthcare organizations alike.

PHIPA Administrative Monetary Penalty

PHIPA Administrative Monetary Penalty

 436 Patient Records. One Clerk. A $2,000 Fine. What Your Organization Needs to Know.

PHIPA Decision 334 from the Information and Privacy Commissioner of Ontario is a wake-up call for every health organization.

A hospital clerk spent six months snooping through the personal health information of 436 patients. She lost her job and was personally fined $2,000.

The message is clear: having privacy policies on paper is not enough. Organizations must ensure that staff understand and follow those policies—and be able to prove it. When they cannot, patients lose trust and organizations face increased regulatory scrutiny

Privacy Breach Nuggets takes real cases and turns them into practical lessons for privacy officers, organizations, and healthcare or public sector institutions. Let’s break down what happened, what the decision found, and how these lessons apply to privacy and records management programs.

What Happened

A patient services clerk at the Children’s Hospital of Eastern Ontario (CHEO) inappropriately accessed the personal health information (PHI) of 436 patients between March and September 2024. The breach came to light when a nurse contacted CHEO’s Privacy Office with questions about her stepchild’s care. The Privacy Office became concerned about how the nurse appeared to know information she should not have known. An audit revealed that a clerk working in the same unit had accessed the child’s record without authorization.

A broader investigation showed that the clerk had accessed:

  • Her own health record
  • Family members’ records
  • Hundreds of other patient records

The information viewed included demographic details, appointment histories, clinical notes, test results, and referral information.

Managing the Breach

We can analyze the hospitals and clinic’s response using the 4-Step Response Plan.

Step 1 – Spot and Stop

The first step is to recognize that a privacy breach has occurred and immediately stop further unauthorized access.

A privacy breach occurs when personal health information is lost, accessed, used, disclosed, or destroyed without authorization.

In this case, CHEO’s Privacy Office received a tip on September 10, 2024, when a nurse raised concerns about her stepchild’s health information.

Step 2 – Investigate

CHEO acted quickly:

  • Conducted an initial audit
  • Placed the clerk on administrative leave
  • Revoked access to the electronic health record system
  • Expanded the audit to six months of activity
  • Conducted formal interviews and justification exercises

The investigation confirmed that the clerk had accessed 436 patient records without authorization.

There was no evidence that she copied, disclosed, or financially benefited from the information.

Remember: Simply viewing a patient record without a legitimate need to know is a privacy breach.

CHEO also confirmed that the clerk had completed initial privacy training and had signed a confidentiality agreement upon hire and a renewal in January 2023.

Step 3 – Notify

When a privacy breach occurs, the right people must be informed promptly.

Internally, notify your Privacy Officer and Custodian immediately.

CHEO reported the breach to the Ontario IPC on October 15, 2024.

CHEO initially notified 189 affected patients by mail. After a more extensive audit identified additional affected individuals, the hospital sent a further 107 notification letters in April 2025. Where current addresses were unavailable, notification letters were added to patient files for delivery at the next visit.

Step 4 – Prevent the Breach from Happening Again

After containing the incident, organizations must take steps to reduce the likelihood of recurrence.

CHEO:

  • Implemented their progressive discipline process.
  • Terminated the clerk’s employment on October 24, 2024.
  • Conducted proactive audits twice monthly for six months.
  • Implemented a comprehensive staff re-training initiative.
  • Reinforced the importance of appropriate access and confidentiality.

Commissioner’s Investigation

The Ontario IPC reviewed the incident and imposed Ontario’s second Administrative Monetary Penalty (AMP) under PHIPA.

An AMP is a financial penalty that the IPC can impose without commencing a court prosecution. The purpose is to encourage compliance and ensure that individuals or organizations do not benefit from privacy violations.

Under the PHIPA AMP regulations:

  • Individuals may be fined up to $50,000
  • Organizations may be fined up to $500,000

In this case, the clerk was ordered to pay $2,000 personally.

CHEO was not fined, but the Commissioner issued two formal recommendations to improve the organization’s ability to monitor, track, and document:

  • Annual privacy training completion
  • Annual confidentiality agreement renewals


Demonstrable Accountability

One of the most important lessons from this decision is the concept of demonstrable accountability.

It is not enough to say that staff are trained and confidentiality agreements are renewed annually.

You must be able to prove it.

In this case, CHEO had strong privacy policies and procedures, but it could not produce documented evidence that the employee had completed her 2024 privacy training or re-signed confidentiality agreements in 2023 and 2024.

The Commissioner summarized this principle clearly:

Organizations must “say what they will do, and then do what they say.”

Take-Aways

✅ A privacy breach can start with one suspicious question–train staff to pay attention and speak up.

✅ Having privacy policies is not enough; you must be able to prove your staff are following them.

✅ Track and document annual privacy training and confidentiality agreement renewals for every single staff member.

✅ Curiosity snooping is a serious breach, even when there is no intention to disclose the information.

✅ Simply viewing a patient record without a legitimate need to know is a privacy breach.

Call to action

Want to strengthen your privacy breach response and accountability program?

Join Kayla Das and Jean L. Eaton for our How to Manage a Privacy Breach in Your Canadian Practice Workshop, where we provide practical tools, templates, and training to help your organization respond confidently to privacy incidents and demonstrate compliance.

Reference

Information and Privacy Commissioner of Ontario. PHIPA Decision 334. April 23, 2026. https://decisions.ipc.on.ca/ipc-cipvp/phipa/en/522336/1/document.do

Privacy Breach Nugget: When Patient “Success Stories” Become a Privacy Breach

Privacy Breach Nugget: When Patient “Success Stories” Become a Privacy Breach

​When Patient “Success Stories” Become a Privacy Breach

Privacy Breach Nugget

Ever wonder how privacy breaches happen—and what you can do to stop them? Privacy Breach Nuggets takes real cases and turns them into practical lessons for privacy officers, clinics, and healthcare practices. Let’s unpack today’s case and explore what went wrong, what worked, and how you can apply these insights to protect patient information.

What Happened

Cadia Healthcare Facilities, which is a rehabilitation, skilled nursing, and long-term care services provider with 5 locations located in Delaware, US.

Cadia posted patient names, photographs, and detailed health information on its public-facing website as part of a marketing campaign featuring patient “success stories.” These disclosures were made without obtaining valid written authorization from the patients whose information appeared on the website.

4 Step Privacy Breach Response

Cadia’s management of the privacy breach can be examined using the 4 Step Response Plan framework.

Step 1 – Spot and Stop

Cadia had procedures that required employees to obtain a written consent from patients before sharing their testimonials. Despite this, the Office of Civil Rights (OCR) received a complaint in September 2021 alleging that patient information had been disclosed without authorization.

OCR’s investigation ultimately confirmed that the protected health information (PHI) of 150 patients had been disclosed without proper authorization. Cadia was formally notified of these findings in February 2022.

Step 2 – Investigate

Cadia conducted an internal investigation and on March 2022 removed all the success stories from their social media and website and ended the marketing campaign.

However, during this process, the organization deleted the content before confirming which patients had valid written consent on file, making it more difficult to accurately determine the full scope of unauthorized disclosures.

Step 3 – Notify

Cadia initially failed to notify affected patients of the privacy breach, as required. Notification obligations were later addressed as part of the enforcement process. A public notice regarding the breach can now be found on the Cadia website.

Step 4 – Prevent the Breach from Happening Again

According to the OCR settlement details:

  • Cadia agreed to pay a $182,000 USD penalty
  • A Corrective Action Plan (CAP) was imposed, including two years of OCR monitoring and reporting
  • Cadia failed to properly implement its existing administrative privacy policies
  • Cadia is required to:
    • Revise its privacy policies and procedures
    • Provide privacy training to all staff, including marketing personnel
    • Implement stronger authorization processes before using patient information for marketing
  • Cadia must now notify all affected individuals whose PHI was disclosed without authorization


Website and Social Media Tips

Custodians are responsible for ensuring that patients’ health information is collected, used, and disclosed in compliance with health privacy legislation, such as Alberta’s Health Information Act (HIA) and Ontario’s Personal Health Information Protection Act (PHIPA).

It’s also important to ensure your practices align with professional college standards related to advertising, professionalism, and confidentiality.

Here are key questions to include in your website and social media compliance checklist before collecting or using patient testimonials:

  • What is your clinic’s approval process before content is posted online?
  • Has the patient provided written consent for their information to be used?
    • If a photograph is included, does the consent explicitly authorize the use of images?
  • Who authorizes the content before it is published?
    • For example: the healthcare provider, lead custodian, social media lead, or privacy officer?
  • Before posting, has the content been reviewed for compliance with:
    • Health privacy legislation?
    • Professional college standards?
  • Does your marketing vendor understand your privacy obligations?
    • Do you have a written agreement in place requiring the vendor to protect the confidentiality of personal health information?

Also See

Is your website secure? Take the Website Self-Assessment from Elevated Business Solutions.

Do you have a website for your healthcare practice in Ontario? PHIPA Website Guide from Elevated Business Solutions will help you.

Take-Aways

The Cadia case is a reminder that policies alone are not enough. Clinics must ensure that privacy requirements are understood, followed in practice, and applied consistently across all teams, including marketing and external vendors. Taking the time to review your website and social media practices now can help prevent a costly and public privacy breach later.

You May Also Be Interested In

Medical Secretary Fined for Unauthorized Access And Disclosure to Health Information

3rd Largest Fine Ever Under the HIA

References

Cadia Healthcare Facilities. Notice of Success Story Incident. https://cadiahealthcare.com/wp-content/uploads/2025/06/Cadia_Notice-1.pdf

Health and Human Services. HHS’ Office for Civil Rights Settles HIPAA Investigation of Cadia Healthcare Facilities for Disclosure of Patients’ Protected Health Information. 2025Sept30. https://www.hhs.gov/press-room/ocr-settles-hipaa-with-cadia-healthcare-facilities.html

Help Me With HIPAA. Did Anyone Even Ask If It Was OK? – Ep 531 podcast. 2025Oct17 https://helpmewithhipaa.com/did-anyone-even-ask-if-it-was-ok-ep-531

Privacy Breach Nugget: Why Documentation Matters in Privacy Breach Investigations

Privacy Breach Nugget: Why Documentation Matters in Privacy Breach Investigations

Investigation Tips Following the NWT Health Authority Incident

When employees make mistakes that result in a privacy breach, the custodian is held responsible to ensure that appropriate investigations are performed. This includes appropriate documentation of the privacy breach incident and sanctions when indicated.

The NWT Information and Privacy Commissioner (IPC) opened an investigation into the Northwest Territories Health and Social Services Authority (NTHSSA) after a reported privacy breach in 2024. This review aimed to assess whether the health authority had adequate safeguards in place to investigate and prevent similar future incidents.

Privacy Breach Nuggets takes real cases and turns them into practical lessons for privacy officers, clinics, and healthcare practices. Let’s dive into what went wrong, what worked, and how you can apply these insights to strengthen your privacy program.

What Happened

In April 2024, a patient filed a complaint with the nurse-in-charge at a health centre in the Northwest Territories. The complaint alleged that a clerk had inappropriately shared the patient’s personal health information with a family member during a casual conversation.

The nurse-in-charge apologized to the patient and escalated the issue to the regional manager. The clerk denied disclosing the health information, but the health authority concluded the incident had indeed occurred.

The Commissioner emphasized that there was no ill intent, stating:

“The interaction between the clerk and the sister was spontaneous and indicates a simple lapse in judgment.”

Managing the Breach

The NTHSSA’s management of the privacy breach can be examined using the 4 Step Response Plan.

Step 1 – Spot and Stop

The privacy breach was identified by the patient and reported to the nurse in charge and escalated to the regional manager.

Step 2 – Investigate

An investigation was initiated. While the clerk denied the allegation, the health authority determined a breach had occurred.

However, the Commissioner noted a serious concern: the investigation was poorly documented. If notes were taken, they could not be located or produced during the review.

Step 3 – Notify

The patient and NTHSSA (the custodian) was aware of the breach. No further notification was required.

Step 4 – Prevent the Breach from Happening Again

The health authority directed the clerk to:

  • Complete updated privacy training
  • Review the oath of office
  • Review patient confidentiality policies

No further disciplinary action was taken.

Commissioner’s Investigation

The IPC made several key recommendations:

  • Equip investigators: Ensure staff who investigate privacy breaches are properly trained and supported to conduct effective, timely, and well-documented investigations.
  • Enforce sanctions: Ensure managers understand the range of disciplinary options available and are aware of their obligation to apply reasonable disciplinary measures when warranted.
  • Annual privacy training: Reinforce the Mandatory Training Policy by ensuring all employees complete refresher privacy training every year.
  • Use real examples: Incorporate this privacy breach as a case study in future privacy training to help employees understand their obligations—at work and outside of work.

Take-Aways

Annual privacy training is not enough.

Training must include real-world, job-relevant examples and emphasize how privacy rules apply in everyday situations.

When employees make mistakes, it’s the custodian’s responsibility to lead an appropriate and well-documented investigation—not just revisit outdated training.

A strong privacy culture includes tools, training, and clarity. Equip your investigators, privacy officers, and managers with the skills they need to respond appropriately.

For more on how to manage privacy-related employee errors, listen to the podcast:

Managing Employees When They Make Mistakes – Episode #105

Need Help Training Your Privacy Team?

Ask me about Practical Privacy Officer Strategies training to strengthen your internal investigation process and build a more resilient workplace.

Reference

NWT IPC File Number: 24-950-6 on April 4, 2025Northwest Territories Health and Social Services Authority (Re), 2025 NTIPC 97 (CanLII), <https://canlii.ca/t/kc0s6>, retrieved on 2025-06-09

You May Also Be Interested In

Medical Secretary Fined for Unauthorized Access And Disclosure to Health Information

3rd Largest Fine Ever Under the HIA


